A general dentist refers a patient to an oral surgeon for a complex extraction when a tooth cannot be safely removed using standard non-surgical methods due to severe impaction, root curvature, structural breakage below the gum line, or close proximity to vital nerves and sinus cavities. Oral and maxillofacial surgeons possess specialized hospital residency training, advanced 3D surgical imaging capabilities, and deep sedation options designed to manage high-risk anatomical factors and complex medical histories safely. Seeking specialist care ensures that complicated surgical removals are executed with precision while protecting surrounding bone tissue for future restorative procedures.
What Is a Complex Tooth Extraction?
A complex extraction—also clinically classified as a surgical extraction—is a specialized procedure required when a tooth cannot be mobilized and elevated through simple mechanical leverage. While routine extractions involve teeth that are fully erupted above the gumline with straightforward root anatomy, complex cases involve teeth that are structurally compromised, trapped beneath alveolar bone, or mechanically locked within the jaw.
When an individual needs to get a tooth removed under challenging clinical circumstances, general dentists evaluate whether standard forceps and elevators will suffice. If the procedure requires incising soft tissue, sectioning the tooth into multiple fragments, or removing cortical bone, it transitions from a simple procedure to a surgical operation best managed by a board-certified oral surgeon.
How Does a Surgical Extraction Differ from a Simple Extraction?
Understanding the clinical differences between extraction types helps clarify why a specialist referral is necessary:
- Simple Extractions: Performed under local anesthesia on visible, fully emerged teeth with intact coronal structure. The periodontal ligament is loosened using standard elevators, and forceps gently luxate the tooth from the socket without incisions.
- Surgical Extractions: Performed under local anesthesia, nitrous oxide, IV moderate sedation, or general anesthesia. The practitioner creates a surgical flap in the gingival tissue to expose the alveolar ridge, uses surgical handpieces to relieve obstructing bone, divides divergent or hooked roots, and sutures the surgical site to facilitate primary healing.
Why Do General Dentists Refer Patients to an Oral Surgeon?
General dentists serve as primary care providers for restorative, preventive, and routine dental needs. However, their referral to an oral and maxillofacial surgeon is driven by a commitment to patient safety, structural preservation, and clinical risk mitigation.
1. Proximity to Vital Nerves
The lower jaw houses the inferior alveolar nerve and the lingual nerve, which transmit sensory feeling to the lower lip, chin, and tongue. When mandibular molars or deeply impacted third molars have roots that impinge upon, wrap around, or run adjacent to the mandibular canal, standard extraction methods carry a risk of nerve compression or transection. Oral surgeons utilize specialized techniques—such as coronectomy or micro-surgical sectioning—to eliminate dental pathology while prioritizing nerve protection and minimizing risks of oral surgery.
2. Maxillary Sinus Proximity
The roots of upper molars and premolars frequently extend directly beneath the floor of the maxillary sinus cavity. In some anatomical variations, only a paper-thin layer of bone—or merely the sinus Schneiderian membrane—separates the root apex from the sinus floor. Attempting a routine extraction on these teeth can cause an accidental root displacement into the sinus cavity or create an oroantral fistula (an opening connecting the oral cavity to the sinus). Oral surgeons are trained to carefully extract sinus-adjacent teeth and perform immediate surgical membrane closures if an opening occurs.
3. Severely Impacted or Ankylosed Teeth
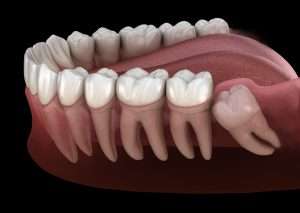
Teeth that fail to erupt properly often become wedged against neighboring roots or encapsulated within dense bone. Identifying patients who need specialist care involves recognizing the signs you need wisdom teeth removal before impaction leads to follicular cysts, pericoronitis, or root resorption on adjacent healthy molars. Furthermore, teeth that are ankylosed—where the tooth root has fused directly to the surrounding bone due to chronic inflammation or trauma—lack a flexible periodontal ligament, making surgical bone removal mandatory for safe extraction.
4. Complex Root Curvature and Fragile Crown Structure
Teeth with dilacerated (severely curved or hooked) roots, multiple divergent roots, or hypercementosis (excessive cementum buildup creating bulbous roots) cannot be pulled vertically without fracturing bone or root tips. Additionally, teeth that have suffered extensive subgingival decay or severe trauma often fracture at or below the bone level. When no visible tooth structure remains for standard dental forceps to grasp, an oral surgeon must surgically trough the bone to retrieve the retained root apices atraumatically.
5. Advanced Patient Age and Bone Density
Age plays a direct role in extraction complexity and bone resilience. Clinical studies show that scheduling wisdom teeth removal between the ages of 17 and 25 offers significant advantages, as root structures are only two-thirds formed and the surrounding jawbone is more pliable. Conversely, evaluating extracting wisdom teeth in adulthood requires surgical management because mature jawbone becomes increasingly dense, roots fully anchor, and healing times lengthen, making the intervention inherently more complex.
6. Pre-Existing Medical Conditions and Systemic Health Factors
Patients with compromised health profiles or specific medical therapies require advanced surgical monitoring. Indications for oral surgery management include:
- Patients taking anticoagulant or antiplatelet medications who face elevated bleeding risks.
- Individuals on antiresorptive therapies (such as bisphosphonates for osteoporosis or oncology care) who carry a risk of medication-related osteonecrosis of the jaw (MRONJ).
- Patients with cardiovascular disease, uncontrolled hypertension, or severe diabetes requiring continuous vital sign monitoring throughout the procedure.
- Individuals with underlying structural jaw discrepancies or craniofacial concerns who may later require corrective treatment like orthognathic surgery.
What Advanced Technologies and Techniques Do Oral Surgeons Use?
Oral and maxillofacial surgery practices are uniquely equipped with diagnostic, surgical, and anesthetic infrastructure that exceeds standard dental office configurations.
3D Cone Beam Computed Tomography (CBCT) Imaging
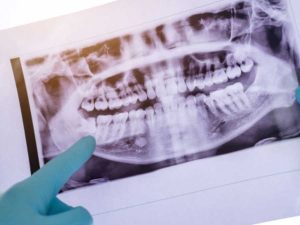
Standard two-dimensional periapical or panoramic X-rays flatten anatomical structures, obscuring root depth, cortical bone thickness, and precise nerve canal spatial relationships. Advanced practices deploy 3D CBCT imaging to produce high-resolution volumetric reconstructions of the maxillofacial skeleton. Surgeons use this 3D data to map surgical trajectories, measure root proximity to the mandibular canal within fractions of a millimeter, and plan incisions before initiating surgery.
Hospital-Grade Sedation and Advanced Anesthesia Options
A complex extraction involving extensive bone manipulation can cause physical discomfort and psychological stress if performed solely under local numbing injections. Oral surgeons complete rigorous training in outpatient anesthesia delivery, allowing them to provide a full spectrum of sedation modalities. By reviewing comprehensive guides on choosing the right anesthesia for oral surgery, patients can select between nitrous oxide, intravenous (IV) moderate sedation, or deep general anesthesia to ensure complete comfort throughout lengthy surgical sessions.
How Does a Surgical Extraction Protect Future Dental Implants?
When a non-restorable tooth is extracted, preserving the structural volume of the surrounding alveolar bone is critical for future tooth replacement therapies. If a tooth is removed aggressively, the delicate buccal bone plate can fracture, resulting in severe ridge collapse and bone resorption.
To prepare the site for permanent restoration using dental implants, oral surgeons execute atraumatic extractions designed to keep the bone walls intact. Simultaneously, the surgeon can perform immediate socket preservation by placing mineralized bone matrix into the void. Utilizing bone grafting to build a strong foundation prevents natural bone atrophy and ensures sufficient vertical and horizontal bone dimensions for stable implant integration.
What Should Patients Expect During Consultation and Recovery?
A surgical referral begins with a comprehensive pre-operative consultation. During this visit, the surgical team reviews the patient’s medical history, assesses 3D scans, evaluates airway anatomy, and discusses anesthesia preferences.
Patients receive detailed instructions outlining how to prepare for oral surgery, including fasting guidelines for IV sedation, medication adjustments, and post-operative transportation requirements. Following the extraction, adherence to recovery protocols—such as applying cold compresses, maintaining soft diet nutrition, avoiding straws to prevent dry socket, and monitoring healing stages—ensures an uncomplicated recovery timeline mirroring standard dental implant recovery milestones.
Frequently Asked Questions
Why can’t my regular dentist perform my tooth extraction?
While general dentists perform routine extractions, they refer complex cases to oral surgeons when teeth are impacted beneath bone, fractured below the gumline, have hooked roots, or sit adjacent to nerves and sinus cavities. Oral surgeons possess 4 to 6 years of specialized surgical residency training and hospital-grade equipment specifically tailored for complex procedures.
Is a surgical tooth extraction painful?
No, the extraction procedure itself is not painful. Oral surgeons utilize profound local anesthesia along with advanced sedation options—such as IV conscious sedation or general anesthesia—ensuring patients feel no pain or distress during the surgery. Post-operative discomfort is managed effectively with prescribed or over-the-counter pain medications and detailed home-care protocols.
What is the difference between an oral surgeon and a general dentist?
A general dentist completes four years of dental school to provide general oral healthcare, restorative treatments, and preventive care. An oral and maxillofacial surgeon completes dental school plus an additional 4 to 6 years of hospital-based surgical residency, receiving intensive training in complex bone and soft tissue surgery, anesthesia administration, trauma care, and pathology.
How long does it take to recover from a complex surgical extraction?
Initial soft tissue healing typically takes 7 to 14 days, during which swelling and mild soreness peak within the first 48 to 72 hours before subsiding. Complete underlying bone remodeling inside the extraction socket generally takes between 3 to 6 months, after which the site is fully prepared for restorations such as dental implants.
What happens if a complex tooth is not extracted?
Leaving a severely damaged, infected, or impacted tooth untreated can result in spreading dental abscesses, systemic infection, localized bone loss, damage to adjacent tooth roots, and the development of cysts or tumors within the jawbone.