Maxillofacial surgery is a specialized medical and dental discipline that focuses on diagnosing and surgically treating structural, functional, and aesthetic disorders of the face, jaws, teeth, mouth, and neck. Key procedures include orthognathic corrective jaw surgery, temporomandibular joint (TMJ) reconstruction, bone grafting, dental implant placement, and pathological resections. These interventions restore proper mastication and airway volume, alleviate chronic facial pain, repair skeletal trauma, and preserve long-term oral-facial integrity.
What Is Oral and Maxillofacial Surgery?
Oral and maxillofacial surgery bridges the gap between dental science and medical surgery. Practitioners in this specialty undergo rigorous hospital-based residency training following dental and medical degree tracks. This multidisciplinary training equips surgeons to manage complex conditions affecting the hard and soft tissues of the head, neck, face, and jaw region.
The scope of maxillofacial surgery extends well beyond basic exodontia. It involves the correction of complex craniofacial abnormalities, the realigning of skeletal anatomy, the management of severe facial trauma, surgical reconstruction of degenerated joints, and the diagnosis and excision of benign and malignant tumors. Surgical interventions within this field prioritize both structural rehabilitation and aesthetic symmetry to maintain overall physiological function.
What Are the Core Procedures in Maxillofacial Surgery?
Maxillofacial surgical interventions encompass a diverse array of specialized techniques tailored to the specific anatomical and physiological needs of each patient. From skeletal realignment to cellular regeneration, each procedure serves a defined clinical objective.
How Does Orthognathic (Corrective Jaw) Surgery Work?
Orthognathic surgery is indicated when the upper jaw (maxilla), lower jaw (mandible), or both fail to align properly with each other or with the cranial base. While standard orthodontic treatment repositions teeth within the alveolar bone, it cannot alter underlying skeletal discrepancies. When dental malocclusion stems from skeletal disharmony, corrective jaw surgery physically repositions the bone.
Surgeons perform precise osteotomies—controlled surgical cuts into the bone—under general anesthesia to segment and reposition the maxilla or mandible. Advanced three-dimensional digital imaging and computer-aided surgical simulation enable sub-millimeter precision when planning these skeletal shifts. Rigid internal fixation, utilizing biocompatible titanium plates and screws, stabilizes the repositioned segments during the osseous healing phase.
The clinical benefits of orthognathic surgery include:
- Restoration of Masticatory Function: Normalizing dental occlusion ensures balanced chewing forces, reducing uneven tooth wear and gastrointestinal strain caused by poorly masticated food.
- Speech Articulation Improvement: Correcting severe overbites, underbites, or open bites eliminates phonetic deficits caused by improper tongue-to-tooth contact.
- Airway Expansion: Maxillomandibular advancement pulls the tongue base and associated pharyngeal soft tissues forward. This expands the upper airway diameter and serves as a highly effective, definitive treatment for severe obstructive sleep apnea.
- Facial Symmetry and Harmony: Realigning the skeletal base balances facial proportions and supports proper soft tissue drape.
How Are Temporomandibular Joint (TMJ) Disorders Managed Surgically?
The temporomandibular joint is a bilateral ginglymoarthrodial joint connecting the mandibular condyle to the temporal bone of the cranium. It enables both rotational hinging and translational sliding movements necessary for speech and chewing. Internal derangement, osteoarthritis, ankylosis, or traumatic damage to the fibrocartilaginous articular disc can cause severe dysfunction, audible clicking, jaw locking, and debilitating myofascial pain.
When non-surgical therapies fail to relieve chronic joint dysfunction, maxillofacial surgeons utilize progressive surgical modalities:
- Arthrocentesis: A minimally invasive procedure involving the cannulation of the upper joint space with sterile needles to lavage inflammatory mediators, break micro-adhesions, and introduce therapeutic lubricants.
- TMJ Arthroscopy: Insertion of an endoscope to directly visualize the intra-articular structures, debride necrotic tissue, and reposition displaced articular discs.
- Open Joint Arthroplasty and Total Joint Replacement: Used for severe degenerative joint disease or ankylosis. The damaged anatomical structures are surgically reconstructed or replaced with customized prosthetic condylar and fossa components.
What Role Do Bone Grafting and Sinus Lifts Play in Facial Reconstruction?
Following tooth loss, trauma, or pathology, the alveolar bone naturally undergoes disuse atrophy and resorption due to the absence of mechanical load. Insufficient bone volume compromises the aesthetic profile of the face and prevents the secure placement of dental implants. Maxillofacial bone grafting restores vertical height and horizontal width to deficient bony ridges.
Surgical protocols utilize several grafting matrices:
- Autogenous Grafts: Bone harvested directly from the patient (such as the mandibular ramus, symphysis, or iliac crest), offering optimal osteogenic and osteoinductive properties.
- Allografts and Xenografts: Biocompatible donor human or bovine bone matrices that provide a safe osteoconductive scaffold for host cellular ingrowth.
- Recombinant Bone Morphogenetic Protein (rhBMP-2): Advanced biologic proteins that actively stimulate native stem cells to differentiate into osteoblasts, accelerating de novo bone growth without secondary harvest sites.
In the posterior upper jaw, close proximity to the maxillary sinus cavity often restricts available vertical bone height. A sinus lift (sinus floor augmentation) gently elevates the Schneiderian sinus membrane through a lateral or crestal window, placing graft material beneath it. This creates a solid, vascularized foundation of natural bone suitable for long-term implant anchorage without compromising sinus health. Evaluating symptoms like nasal congestion is important in this context, as clinicians often assist patients in distinguishing allergies from respiratory infections prior to evaluating midface or sinus-related surgical viability.
Why Are Dental Implants the Preferred Method for Tooth Replacement?
Dental implants serve as prosthetic tooth roots embedded directly into the alveolar process. Constructed from commercially pure titanium or zirconia, implants undergo osseointegration—a structural and functional biological union between the living bone and the surface of the implant fixture.
Unlike conventional dental bridges, which require the irreversible reduction of adjacent healthy teeth, or removable dentures that accelerate ridge resorption, dental implants transmit functional masticatory forces directly into the surrounding bone. This physiological stimulation preserves bone mass, prevents premature facial aging, and provides exceptional biomechanical stability for crowns, bridges, and full-arch prostheses.
How Are Wisdom Teeth and Pathological Conditions Treated?
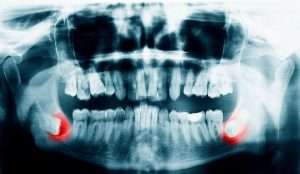
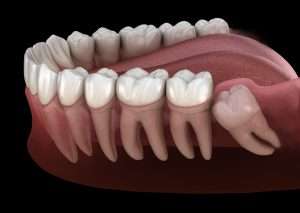
Third molars, commonly known as wisdom teeth, represent the final set of teeth to erupt into the oral cavity. Due to evolutionary reductions in human jaw size, these molars frequently become impacted against adjacent bone or soft tissue, leading to several clinical complications:
- Pericoronitis: Painful, acute bacterial infection of the gum tissue overlying a partially erupted tooth.
- Root Resorption and Decay: Damage caused to the adjacent second molar due to persistent localized pressure and plaque accumulation.
- Odontogenic Cysts and Tumors: Formation of fluid-filled follicular cysts that can expand asymptomatically, destroying adjacent jawbone and compromising nerve pathways.
Surgical extraction of impacted third molars eliminates these hazards. When other essential teeth, such as maxillary canines, become impacted, maxillofacial surgeons perform surgical exposure and bonding, working alongside orthodontists to guide the tooth safely into the dental arch.
Maxillofacial surgeons also evaluate and excise suspicious oral lesions, such as leukoplakia (white lesions), erythroplakia (red lesions), and salivary gland tumors. Biopsies are performed for precise histological evaluation to rule out dysplasia or malignancy. Determining the underlying pathology is vital, as early symptoms can mimic other common head and neck presentations; examining the underlying causes of persistent throat and jaw pain ensures appropriate differentiation between mucosal infections and deeper anatomical issues.
What Is Pre-Prosthetic Surgery?
Before a patient can receive partial or complete dental prosthetics, the underlying oral architecture must be prepared to support the device without irritation. Pre-prosthetic surgery refines the shape of the alveolar ridge by smoothing uneven bony contours (alveoloplasty), removing benign bony overgrowths (tori), and reducing excessive fibrous tissue (epulis fissuratum). This surgical refinement provides a stable, uniform surface that prevents painful pressure ulcers and ensures comfortable prosthetic retention.
How Do Anesthesia Protocols and Patient Safety Standards Operate?
Given the invasive nature and delicate anatomical working field of maxillofacial operations, comprehensive pain control and airway management protocols are mandatory. Oral and maxillofacial surgeons receive extensive formal hospital training in anesthesiology alongside medical anesthesiologists.
Depending on procedural invasiveness and patient health status, anesthesia options include:
- Local Anesthesia: Targeted neural blockade for minor localized interventions.
- Nitrous Oxide with Local Anesthesia: Inhalation sedation providing mild anxiolysis for simple extractions or soft tissue excisions.
- Intravenous (IV) Moderate-to-Deep Sedation: Pharmacological depression of consciousness that relieves severe anxiety while preserving spontaneous respiratory drive.
- General Anesthesia: Complete, reversible loss of consciousness and airway control, administered in accredited outpatient surgical suites or hospital operating rooms.
Throughout surgical procedures under sedation, strict physiological monitoring is maintained, including continuous electrocardiography (ECG), capnography (end-tidal CO2), pulse oximetry, and automated non-invasive blood pressure tracking. Reviewing patient health history through preparing medical records and pre-appointment documentation ensures that underlying systemic conditions, prescription medications, and anesthesia risks are fully accounted for prior to any surgical event.
When Should Patients Seek Emergency Care Versus Outpatient Surgical Consultation?
Facial and oral health concerns vary significantly in clinical urgency. Recognizing whether a condition necessitates emergency evaluation or scheduled surgical intervention is essential for patient safety and effective care delivery.
Patients experiencing immediate life-threatening symptoms—such as acute facial trauma with airway compromise, rapidly progressive floor-of-mouth swelling (Ludwig’s angina), uncontrollable oral hemorrhage, or fractures of the midface and mandible—require prompt emergency room medical care. Emergency centers possess the trauma-stabilization equipment and acute surgical teams necessary to manage unstable vital signs.
Conversely, non-emergent or subacute oral conditions are best evaluated in dedicated outpatient settings. Patients seeking treatment for impacted wisdom teeth, gradual jaw misalignment, chronic TMJ clicking, dental implant consultations, or initial assessments for minor oral lesions should schedule targeted specialist consultations. For initial evaluation of minor soft tissue trauma, facial lacerations, or secondary wound care, understanding urgent care vs primary care models enables patients to access rapid, cost-efficient treatment without unnecessarily burdening emergency departments.
Furthermore, recognizing why minor soft tissue cuts and scrapes should not be ignored is critical to preventing systemic infections, especially when facial skin or oral mucosal barriers are broken. Choosing outpatient facilities for baseline diagnostics offers measurable walk-in clinic cost and time efficiencies, ensuring patients receive fast assessments, preliminary diagnostics, and appropriate surgical referrals.
What Are the Primary Long-Term Benefits of Maxillofacial Surgical Interventions?
Maxillofacial surgery produces lasting benefits that enhance overall systemic health, daily physical function, and psychological well-being. By addressing underlying skeletal and structural abnormalities, these procedures provide permanent resolutions rather than temporary symptom management.
- Optimized Nutritional Intake: Restoring full masticatory capacity allows patients to consume balanced, nutrient-dense whole foods without pain or mechanical difficulty.
- Permanent Resolution of Airway Obstruction: Skeletal expansion enlarges airway dimensions, significantly diminishing sleep apnea symptoms, nocturnal desaturations, and daytime fatigue.
- Alleviation of Chronic Craniofacial Pain: Joint debridement, disc stabilization, and occlusal balance relieve tension on masticatory muscles, reducing chronic headaches and facial discomfort.
- Preservation of Skeletal Architecture: Bone grafting and dental implants stop the progressive bone resorption that naturally follows tooth loss, preserving facial contours and structural integrity over a lifetime.
Before undergoing elective maxillofacial reconstructive operations, patients often undergo standard clinical assessments, including pre-procedural health screenings and immunization checks, to establish systemic readiness. Routine access to comprehensive walk-in clinical evaluations and educational materials from medical educational resources empowers individuals to navigate diagnostic pathways with confidence.
Frequently Asked Questions
What is the difference between an oral surgeon and a general dentist?
While general dentists manage preventive care, restorations, simple extractions, and periodontal health, oral and maxillofacial surgeons complete an additional 4 to 6 years of hospital-based surgical residency. This surgical residency includes specialized training in internal medicine, general surgery, anesthesiology, plastic surgery, emergency trauma care, and complex osseous reconstruction.
How long is the recovery period following corrective jaw surgery?
Initial soft tissue healing and acute swelling reduction typically take 2 to 3 weeks, during which patients follow a modified liquid or pureed diet. Complete osseous union of the repositioned jawbones generally takes between 6 and 12 weeks. Most patients return to non-strenuous work or school within 2 to 4 weeks, with full skeletal maturation continuing over several months.
Are bone graft materials used in maxillofacial surgery safe?
Yes. All bone grafting materials—including allografts from human donors, xenografts from bovine sources, and synthetic matrices—undergo rigorous sterilization and demineralization processes regulated by the FDA and tissue banking standards. These processes remove all cellular and viral elements, leaving behind a sterile mineral scaffold that supports the patient’s natural osteogenesis.
Why do impacted wisdom teeth need to be removed if they are not causing pain?
Asymptomatic impacted wisdom teeth can still cause silent, progressive pathology beneath the gum line. This includes the development of dentigerous cysts, root resorption of adjacent second molars, bone loss, and localized periodontal defects. Proactive removal in young adulthood minimizes surgical complexity, accelerates bone regeneration, and prevents severe future complications.
What types of anesthesia are available for maxillofacial procedures?
Surgeons offer local anesthesia, nitrous oxide sedation, intravenous (IV) moderate-to-deep conscious sedation, and general anesthesia. The selected anesthesia modality depends on the surgical complexity, patient health status, and anxiety levels, and is administered in strict accordance with hospital-grade safety protocols.